What a high anion gap indicates
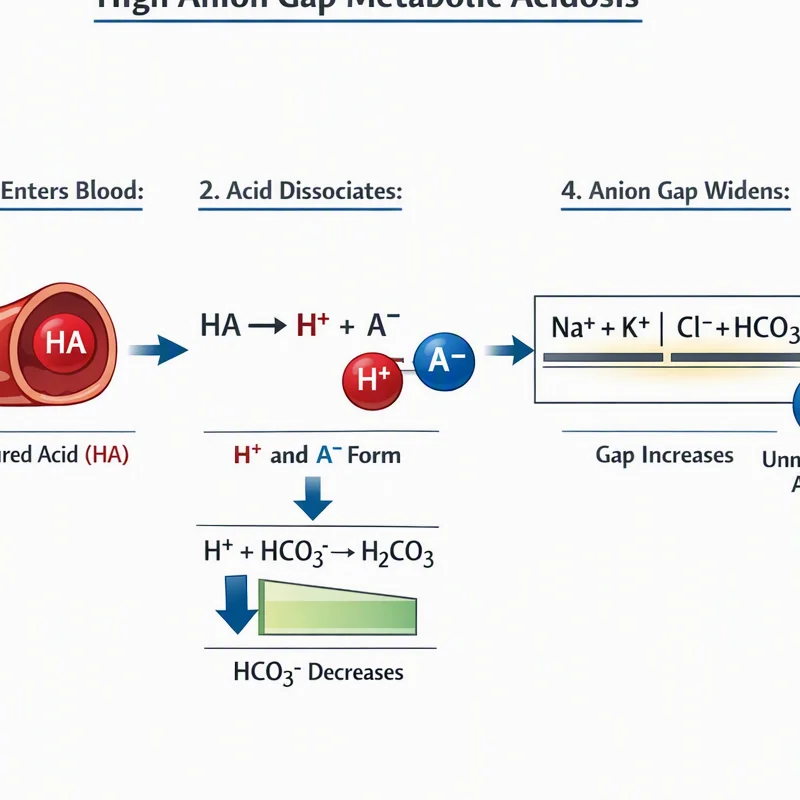
The anion gap is a useful way to evaluate serum chemistry and detect an acid-base disorder. A high anion gap usually points to anion gap metabolic acidosis, which happens when acid accumulates in the body or when normal base is lost. Put simply, the gap rises because of extra unmeasured anions in the blood.
This pattern matters because it limits the differential diagnosis. Rather than looking only at pH, clinicians use the gap as a biochemical marker of acid buildup and possible acid accumulation. A high result can reflect metabolic acidosis from nonserious causes, but it can also be the first sign of poisoning or another critical metabolic derangement.
The concept is closely tied to acid-base balance. When the body produces or accumulates acids faster than it can clear them, bicarbonate is consumed and the gap often rises. This is why a high result is not a diagnosis by itself; it is a clue that informs the next step in the diagnostic workup.
How an Anion Gap Calculator is applied
An Anion Gap Calculator is a simple way to estimate the gap from basic lab values. It uses serum sodium, serum chloride, and serum bicarbonate to use the anion gap formula. In its standard form, it guides clinicians detect a lab abnormality that may not be apparent from symptoms alone.
This tool assists with laboratory interpretation during urgent assessment. If the gap is elevated, the result can suggest a hidden acid load and trigger a more extensive search for the cause. That search often includes checking for toxic ingestion, reviewing medications, and assessing for other conditions that lead to acid buildup.
The calculator is especially useful when the clinical presentation is nonspecific. A patient may have nausea, confusion, shortness of breath, or appear generally ill. The calculator can shape a vague concern into a more focused plan by identifying whether the issue fits a high-gap acid-base disorder.
Although the number is useful, it should always be interpreted alongside the rest of the evaluation. A normal or abnormal result does not exist alone. It must be paired with the history, exam, and related tests such as blood gas analysis and toxin screening when indicated.
Toxins that can cause a high anion gap
Many toxins can produce a increased anion gap by causing generalized acid buildup. The main concerns are ethylene glycol, methanol, salicylates, and propylene glycol. These exposures are significant because they may advance fast and because early treatment can prevent major injury.
These substances are often discussed under the category of toxic alcohols, though not all of them are alcohols in the everyday sense. Some are solvents, some are drugs, and some are breakdown products that create an acid load after they are broken down by the body. The common result is anion gap metabolic acidosis from rising acids.
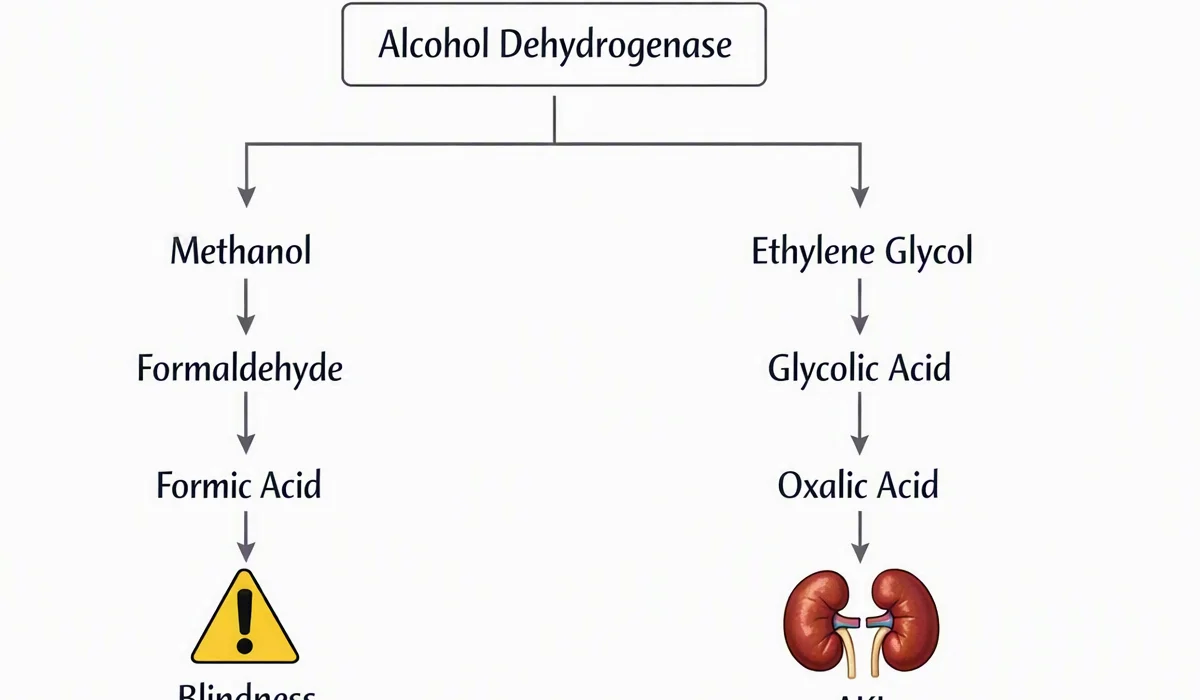
Ethylene glycol is classically linked to antifreeze exposure. It is metabolized into acidic compounds that elevate the anion gap and can injure the kidneys. Methanol is another major toxic alcohol; it is dangerous because its metabolites can damage the optic system and create severe acidosis. Both are medical emergencies.
Salicylates, including aspirin overdose, can also raise the gap. They often create a mixed picture with more than one acid-base abnormality, which can make interpretation harder. Propylene glycol can be seen as a vehicle in some medications and infusions, and in high amounts it may also contribute to acidosis and a increasing gap.
Alcohol-associated poisonings
Toxic ingestions related to alcohols are among the most significant causes to consider when the osmolar gap and anion gap are both abnormal. Methanol and ethylene glycol are the classic examples. Early after exposure, the osmolar gap may be increased because the parent compound is still present. Later, as metabolism proceeds, the anion gap may rise as acidic metabolites accumulate.
This timing matters. A patient may present with a unchanged or only mildly elevated gap early on, then develop a sharp increase later. That is why clinicians rely on repeated assessment, not a single value. The pattern can help separate a toxic alcohol exposure from other forms of metabolic acidosis.
Methanol poisoning often leads to visual disturbances, while ethylene glycol more commonly leads to kidney injury and crystals in the urine. In both situations, the acid-base pattern reflects the same underlying problem: the body is converting a poison into acids faster than it can clear them.
Medication and chemical causes
A toxin-related high gap does not always come from ingesting a toxic alcohol. Salicylates are a major medication cause and can lead to an elevated gap through several mechanisms, including increased acid production and altered metabolism. A person with salicylate toxicity may also show respiratory findings that make the picture more complex.
Propylene glycol is another important chemical cause. It may be found in some IV medications or preparations, and large exposures can cause a clinically significant acid-base disturbance. Although less familiar than methanol or ethylene glycol, it belongs in the workup when an unexplained gap is seen in a hospitalized patient.
Isoniazid is also clinically relevant. Overdose can produce severe neurologic toxicity and metabolic complications, sometimes including acidosis. Because the presentation may evolve quickly, it should remain on the list when the history suggests possible medication ingestion.
Other serious reasons of elevated anion gap acidosis
Ingestions are only part only of the clinical differential. Several non-injury-related disorders also lead to high anion gap states, and they can seem similar on first assessment. The most important include lactic acidosis, ketoacidosis, and renal failure.
Lactic acidosis occurs when tissues are poorly perfused, oxygen delivery is impaired, or metabolism is altered. It is a typical cause of metabolic acidosis and can be seen in shock, severe infection, seizures, or other conditions that produce widespread physiologic stress. Because lactate is an unmeasured anion, it contributes immediately to the gap.
Ketoacidosis is another common cause. It can develop in diabetes, alcohol use, or prolonged fasting. Ketone bodies act as unmeasured anions, generating the same pattern of anion gap metabolic acidosis. The history often reveals the diagnosis, but the lab pattern supports the concern.
Renal failure leads to the kidneys to retain acids and fail to excrete normal metabolic byproducts. Over time, this leads to accumulation of unmeasured acids and a higher gap. In a patient with chronic kidney disease or acute kidney injury, this can imitate toxin-related illness and should be evaluated carefully.
How clinicians tell apart exposure to toxins from different causes
Differentiating toxic ingestion from alternative causes demands a systematic diagnostic workup. The first clues often come from the osmolar gap, an arterial blood gas, and the lactate level. Taken together, these help determine whether the problem is a toxic alcohol, lactic acidosis, ketoacidosis, or another cause of acid-base disturbance.
The osmolar gap is particularly helpful early in toxic alcohol exposure. A high osmolar gap suggests extra low-molecular-weight substances in the blood, such as methanol or ethylene glycol. As metabolism proceeds, the osmolar gap may fall while the anion gap rises. This changing pattern is a classic clue in laboratory interpretation.
An arterial blood gas helps determine the severity of the acidosis and shows whether respiratory compensation is present. A patient may hyperventilate to compensate for metabolic acidosis, lowering carbon dioxide and partially balancing the pH. If compensation is inadequate or the patient is tiring, the risk increases.
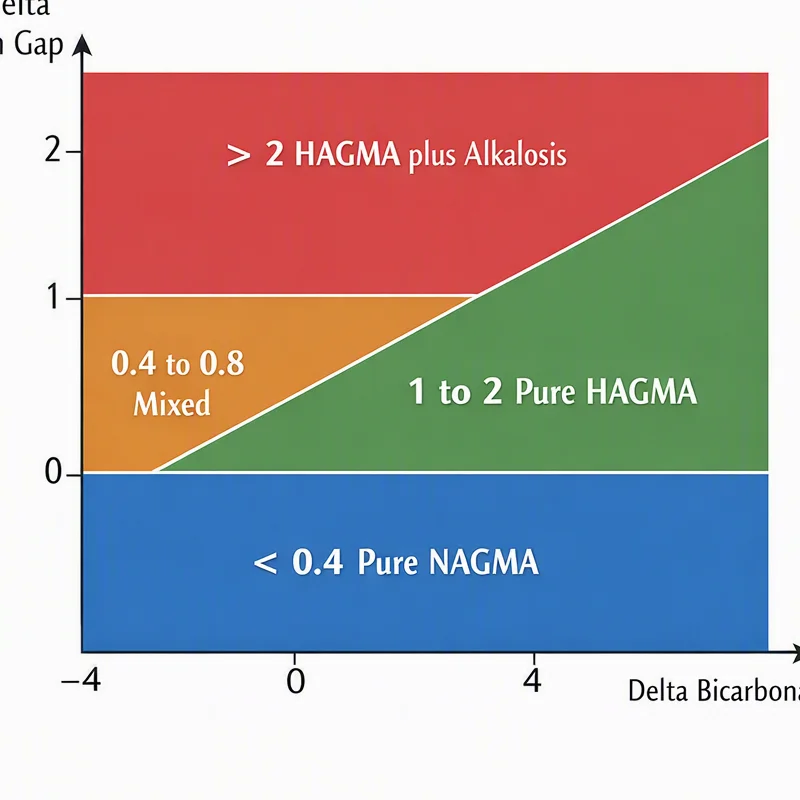
Lactate testing helps differentiate lactic acidosis from toxin-related causes. A very high lactate may explain the gap, but a normal or only mildly elevated lactate should lead clinicians to consider more strongly toxic alcohols, salicylates, ketoacidosis, or renal failure. The full pattern matters more than any single result.
Signs that may suggest a toxic ingestion
The clinical picture of acidosis related to toxins can be varied and nonspecific, but certain symptoms are concerning. Mental status changes is a major warning sign, especially if it appears with a high anion gap and no clear alternative explanation. Confusion, drowsiness, restlessness, or decreased responsiveness may all occur.
Vision changes are particularly concerning in methanol exposure. Patients may describe hazy vision, decreased acuity, or even the feeling that they are “going blind.” This finding should prompt urgent evaluation for toxic alcohol exposure, even before confirmatory testing returns.
Rapid breathing is another important clue. It often reflects respiratory compensation for metabolic acidosis, as the body tries to blow off carbon dioxide. A fast breathing rate may be one of the earliest visible signs that an acid-base disorder is becoming severe.
Other findings can include nausea, vomiting, abdominal pain, prostration, or collapse. Because these symptoms overlap with many illnesses, the lab pattern is essential. When symptoms and labs align, the suspicion for a dangerous ingestion increases significantly.
When a elevated anion gap is a medical emergency
An elevated gap is a medical emergency when it suggests poisoning, severe metabolic acidosis, or swiftly worsening systemic illness. This is most concerning when toxic alcohol exposure is possible, because delays in emergency treatment can lead to blindness, kidney injury, neurologic damage, or death.
Urgent evaluation is also warranted if the patient has altered mental status, severe tachypnea, a rapidly rising gap, or evidence of end-organ injury. In this setting, clinicians may call poison control, consult toxicology, and begin treatment before all confirmatory studies are back.
Management depends on the cause, but early action can be lifesaving. That may include antidotal therapy, correction of acid-base abnormalities, and sometimes dialysis for severe toxic alcohol exposure or profound acidosis. The key point is that a high gap is not just a lab abnormality; it may be a sign of ongoing systemic toxicity.
Any patient with suspected ingestion, especially of toxic alcohols, should be treated as needing urgent evaluation. The combination of a high anion gap, an abnormal osmolar gap, and concerning symptoms should trigger immediate escalation.
Frequently asked questions on toxic causes of high anion gap
What toxic substances commonly lead to a high anion gap?
The most frequent toxin-related causes are methanol, ethylene glycol, salicylates, and propylene glycol. These exposures can create anion gap metabolic acidosis by generating acidic metabolites or https://anion-gap-lookup327.urbanvellum.com/posts/anion-gap-calculation-when-bicarbonate-is-normal interfering with normal metabolism. In real-world evaluation, toxic alcohols are among the most important causes to rule out.
How does an Anion Gap Calculator help identify toxic ingestions?
An Anion Gap Calculator rapidly calculates the gap from serum sodium, serum chloride, and serum bicarbonate. If the result is high, it signals possible hidden acid accumulation and assists in narrowing the differential diagnosis. That makes it helpful when evaluating a possible toxic ingestion or other acid-base disorder.
What is the difference between a high anion gap and an osmolar gap?
The anion gap reflects unmeasured acids in the blood, while the osmolar gap reflects extra dissolved particles that are not accounted for in routine calculations. Toxic alcohols can raise both, but often at different times during metabolism. A high osmolar gap can indicate recent exposure, while a high anion gap suggests acid-forming metabolites have accumulated.
Can aspirin or salicylates cause a high anion gap?
Yes. Salicylates can cause a high anion gap and may also produce a mixed acid-base picture. They are an important cause of metabolic acidosis and should be considered when the history suggests medication overdose or when the clinical presentation includes ringing in the ears, hyperventilation, or confusion.
When does a high anion gap be treated as a medical emergency?
A high anion gap should be treated as an emergency when there is concern for poisoning, severe symptoms, or rapidly worsening acidosis. Signs such as altered mental status, visual disturbances, tachypnea, or a markedly abnormal arterial blood gas warrant urgent evaluation. If toxic alcohol exposure is possible, immediate toxicology-guided treatment may be needed.