What Is the Anion Gap?
The anion gap is a computed value that helps clinicians assess the balance of electrolytes in the blood. It is usually calculated from sodium, chloride, and bicarbonate values on a basic or comprehensive chemistry panel. Because some charged particles are not directly measured, the anion gap acts as a clue to whether there are hidden acids building up in the bloodstream.
A higher-than-normal result suggests an elevated anion gap, which often points to excess acid from organic acids, toxins, or impaired clearance. In basic terms, high anion gap metabolic acidosis means the body has too much acid and not enough buffering capacity, usually reflected by low bicarbonate and changes in blood pH.
One important factor is albumin, the main unmeasured negatively charged protein in plasma. Lower albumin can make the anion gap look artificially normal, so albumin correction is often needed for accurate clinical interpretation. That is why the anion gap should always be viewed in the context of the full lab picture, not as a standalone number.
How an Anion Gap Calculator Aids Recognize Metabolic Acidosis
An Anion Gap Calculator helps translate a set of lab values into a valuable clue for diagnostic evaluation. By entering sodium, chloride, and bicarbonate, the calculator helps determine whether the blood chemistry pattern indicates metabolic acidosis and whether the gap is elevated. This is especially helpful when the issue is not just acid excess, but a distinct type of acid-base disorder.
In practice, an Anion Gap Calculator is used alongside the full blood chemistry panel, an arterial blood gas, and the patient’s symptoms. A low bicarbonate value alone does not explain the cause. The calculator helps separate ordinary bicarbonate loss from acid accumulation due to lactate, ketones, toxins, or reduced kidney clearance.
For clinicians, the calculation supports a systematic approach:
- Establish true metabolic acidosis with bicarbonate and blood pH. Determine whether the anion gap is elevated. Evaluate respiratory compensation on arterial blood gas. Examine the patient for toxin exposure, kidney dysfunction, shock, or infection. Use albumin correction and, when needed, the delta gap to sharpen interpretation.
This kind of organized review matters because high anion gap metabolic acidosis can reflect a life-threatening condition. The calculator does not replace clinical judgment, but it makes the pattern easier to recognize quickly.
Frequent Causes of Elevated Anion Gap Metabolic Acidosis
The main causes of high anion gap metabolic acidosis are disorders that raise acid production or reduce acid excretion. These typically include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each of these creates a distinct clinical pattern, but all can lead to an elevated anion gap.
Identifying the cause begins with asking what type of acid is rising. Is it lactate from poor perfusion? Ketones from accelerated fat metabolism? Retained acids from uremia? Or a poison that breaks down into organic acids? That differential diagnosis drives treatment and urgency.
Lactate Acidosis
Lactic acidosis occurs when lactate accumulates faster than the body can clear it. This is often associated with shock, sepsis, severe hypoxemia, or other forms of tissue hypoperfusion. When cells do not get enough oxygen, they shift toward anaerobic metabolism, which drives up lactate production and lowers pH.
This problem is important because it often signals a serious underlying illness rather than a primary metabolic problem. A rising lactate level may accompany fever, low blood pressure, altered mental status, or organ dysfunction. In many cases, the anion gap is one of the first clues that something is wrong before the full picture becomes obvious.
Diabetic, Alcohol, and Starvation Ketosis
Ketoacidosis develops when the body produces excess ketones, which are acidic byproducts of fat metabolism. The classic form is diabetic ketoacidosis, but alcoholic ketoacidosis and starvation-related ketosis can also raise the anion gap. In all of these, the body is in a state of insufficient usable glucose, leading to increased ketone production.
Diabetes is a significant risk because insulin deficiency allows fat breakdown to increase. Alcohol use can add to this through poor intake, vomiting, and altered metabolism. Starvation or prolonged fasting can also drive the body toward ketone generation. In these situations, the acidosis may be associated by dehydration, abdominal pain, vomiting, or rapid breathing as the body tries to compensate.
Kidney Failure and Uremia
Renal failure can lead to high anion gap acidosis because the kidneys are no longer able to clear acid effectively. As kidney function worsens, acid retention leads to uremia, another common cause of an elevated gap. In many cases, the blood test pattern includes a rising creatinine, abnormal potassium, and other signs of renal impairment.
When chronic kidney disease progresses, the body accumulates nonvolatile acids that should normally be excreted in urine. That acid buildup contributes to metabolic acid buildup and a lower bicarbonate level. Clinicians often look for this cause when a patient has known kidney disease, reduced urine output, or symptoms suggesting long-standing renal dysfunction.
Poisonings and Toxic Ingestions
Several toxins can create a worrying high anion gap pattern. Methanol and ethylene glycol are the classic toxic alcohols, and both can be metabolized into acidic compounds that sharply increase the anion gap. Salicylates are another important cause because they can trigger mixed acid-base abnormalities and raise acid levels.
These cases are especially concerning because they may present with brain-related symptoms, visual changes, vomiting, or rapid breathing before the diagnosis is obvious. A careful history of possible exposure is critical. In many cases, the combination of an elevated gap and the clinical scenario should trigger immediate treatment while confirmatory testing is underway.
Uncommon Causes to Think About
Not all elevated finding comes from the most familiar reasons. Less typical explanations for high anion gap metabolic acidosis include rhabdomyolysis, 5-oxoproline accumulation, propylene glycol ingestion, and D-lactic acidosis. Such causes are prone to miss unless the clinician keeps a broad differential diagnosis.
Rhabdomyolysis can contribute through muscle breakdown and associated metabolic changes. 5-oxoproline acidosis may develop with chronic acetaminophen use in susceptible patients. Propylene glycol is often present in certain IV medications and can be an unrecognized driver of gap elevation. D-lactic acidosis is uncommon but may appear in patients with short bowel syndromes or altered gut bacterial metabolism.
Such explanations matter because the patient may not fit the classic pattern of lactic acidosis or ketoacidosis. If the anion gap is elevated but the usual explanations do not fit, clinicians should reassess medication history, nutritional status, toxic exposures, and chronic medical conditions.
How Clinicians Interpret the output
Interpreting a high anion gap requires more than just identifying a number. Clinicians combine the chemistry panel with an arterial blood gas to verify the degree of acidemia and assess respiratory compensation. They also consider whether the pattern fits a specific acid-base disorder or a mixed disorder.
One key tool is the delta gap, which helps determine whether there is an additional hidden acid-base issue alongside the elevated anion gap. For example, a patient may have both high-gap acidosis and metabolic alkalosis from vomiting, or a combined respiratory problem. This step improves clinical interpretation and prevents missing a second disorder.
Albumin also needs careful attention. Because albumin is a major unmeasured anion, low albumin can mask the size of the gap. That is why albumin correction is often crucial when the measured anion gap seems less striking than the clinical picture suggests.
In practical terms, the interpretation process often includes:
- Establishing metabolic acidosis with bicarbonate and blood pH. Looking for an elevated anion gap. Examining serum electrolytes and blood chemistry panel results. Evaluating lactate, ketones, creatinine, and toxin exposure. Applying the delta gap and albumin correction when appropriate.
When Elevated Anion Gap Acidosis Is an Emergency
A increased anion gap result becomes significantly more urgent when it is accompanied by concerning signs. Signs such as confusion, respiratory distress, or hypotension may indicate severe illness, poor perfusion, or poisoning. In that setting, emergency evaluation is needed without delay.
This is most true when the suspected cause is lactic acidosis from shock or sepsis, diabetic ketoacidosis, severe renal failure, or exposure to methanol or ethylene glycol. These are never conditions to monitor passively. They can worsen quickly and may require hospital-based treatment, fluids, antidotes, dialysis, or intensive monitoring.
Patients should seek urgent care if symptoms are intense or getting worse quickly, if there is a known ingestion, or if the lab abnormality is paired with altered mental status, rapid breathing, chest pain, or collapse. A elevated anion gap can be the initial alert of a potentially life-threatening metabolic problem, but the surrounding symptoms determine how urgent the situation really is.
FAQ About High Anion Gap Metabolic Acidosis
How is defined a high anion gap?
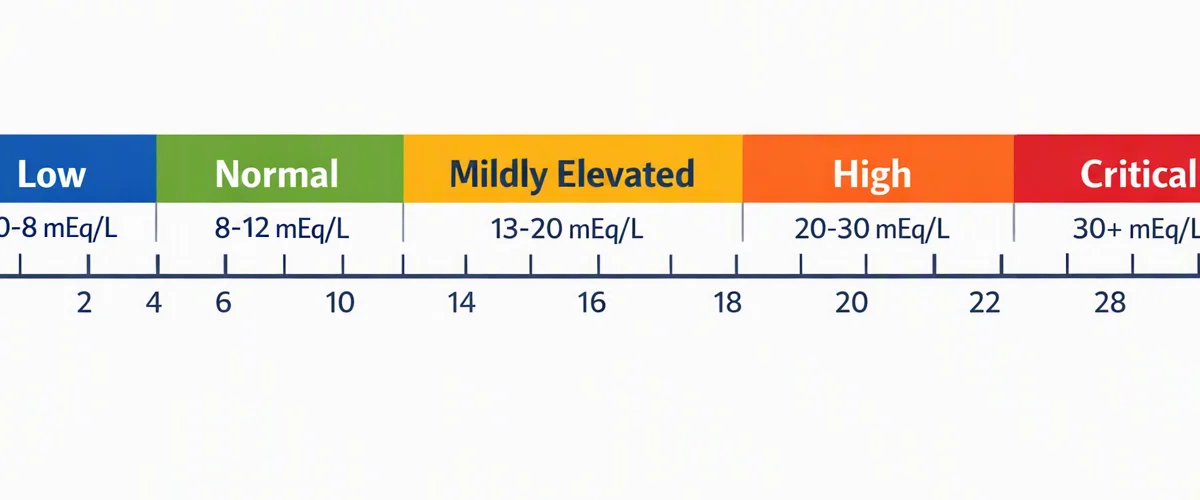
A high anion gap commonly a value above the normal expected range used by the lab, but the exact cutoff can change. The key question is whether the result indicates an elevated anion gap in the context of the patient’s metabolic acidosis, bicarbonate level, and overall clinical interpretation. Since the normal range differs slightly by method, the full diagnostic evaluation matters more than a single universal number.
Which are the most common causes of high anion gap metabolic acidosis?
The primary causes are lactic acid elevation, ketoacidosis, renal failure, and toxic alcohols for example methanol plus ethylene glycol. Aspirin compounds can also be relevant. These conditions cause acid accumulation, reduced bicarbonate, and a larger gap because the body is dealing with excess undetected acids.
How does albumin affect the anion gap calculation?
Albumin is a major unmeasured anionic protein, so decreased albumin can make the anion gap seem falsely within range or less elevated than it really is. For https://anion-gap-calculation.com/special-populations/pregnancy.html this reason albumin correction is essential when assessing the result. When it is not applied, a clinician may miss a genuine high gap state, especially when other signs of metabolic derangement are present.
Can dehydration cause a high anion gap metabolic acidosis?
Dehydration alone does not usually cause a high anion gap, but it can contribute indirectly. Significant dehydration may intensify shock, decrease kidney perfusion, or heighten the likelihood of lactic acidosis and ketoacidosis. So while dehydration is not typically the direct cause, it can be part of the chain that leads to a severe acid-base disorder.
At what point should a high anion gap result be treated as an emergency?
This should be considered an emergency when the patient has disorientation, respiratory distress, dangerously low blood pressure, or additional signs of critical illness, or when there is suspected poison exposure. An elevated anion gap with progressively worsening severity of symptoms may indicate a life-threatening condition that needs immediate immediate assessment. The result should always be interpreted alongside the history, physical exam, and labs rather than on its own.