What an Anion Gap Indicates in Excess Iron
The anion gap is a practical way to evaluate an acid-base imbalance when a patient has a presumed iron overdose. In toxicology, the anion gap helps clinicians determine whether metabolic acidosis is occurring and whether it may suggest significant systemic toxicity. Because iron poisoning can worsen fast, the anion gap is often part of the early emergency assessment alongside the patient’s clinical presentation and serum electrolytes.
An anion gap calculator is not a diagnosis by itself, but it can help assess whether the patient has a high anion gap metabolic acidosis, which may signal a dangerous metabolic derangement. In iron toxicity, this finding can support concern for severe poisoning, especially when paired with vomiting, abdominal pain, hypotension, or altered mental status.
From a practical standpoint, the anion gap helps clinicians calculate and interpret the difference between measured cations and anions in the blood. When the gap rises, it often indicates unmeasured acids in the bloodstream. In the setting of iron poisoning, those acids may include lactate from poor tissue perfusion or other metabolites produced during severe toxicity.
It is important to remember that acid-base balance can shift suddenly in iron overdose. Early on, a patient may have minimal laboratory abnormalities, but as toxicity worsens, the anion gap and other laboratory results may change. That is why the anion gap is best used as part of a more comprehensive diagnostic and risk stratification approach rather than as a standalone screening tool.
Calculating the Anion Gap
The standard anion gap formula uses three key laboratory values: serum sodium, serum chloride, and serum bicarbonate. The most widely used version is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
The calculation is straightforward, but it can provide useful clinical information in a suspected toxic ingestion. When using an anion gap calculator, the clinician records the serum sodium, serum chloride, and serum bicarbonate values obtained from the chemistry panel. The result can assist evaluate whether an acid-base disorder is present and whether further toxicology workup is needed.
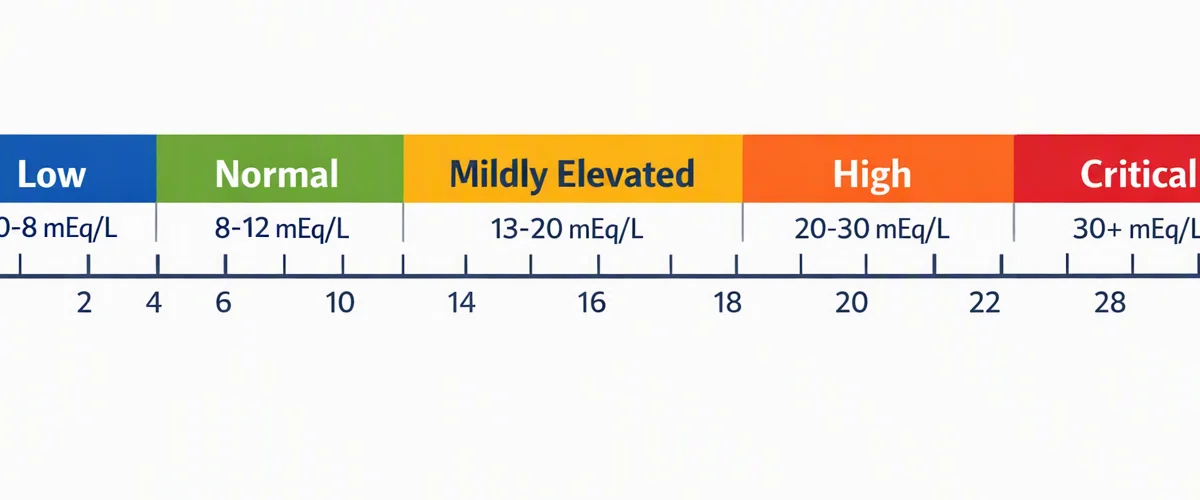
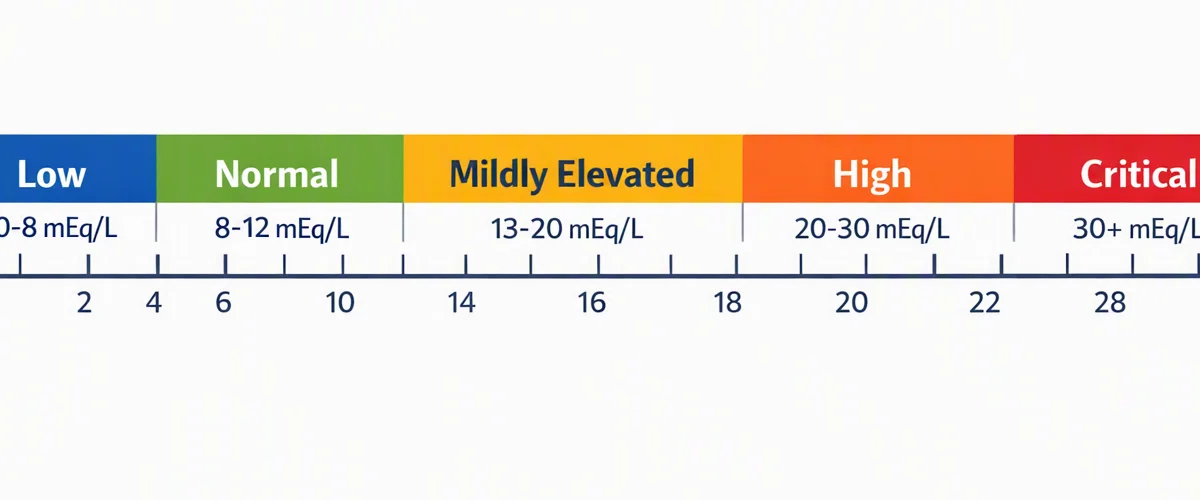
Normal ranges vary by laboratory, but a clearly elevated gap suggests build-up of unmeasured anions. In iron overdose, that can point toward lactic acidosis or an additional severe metabolic disturbance. If the number is only mildly elevated, the result still needs clinical correlation because early iron poisoning can change over time.
Albumin also matters. Since albumin is a major unmeasured anion, low albumin can make the gap appear falsely normal or lower than expected. In that case, an albumin-corrected anion gap may be more informative. This correction is especially useful when the goal is to interpret laboratory results accurately in the context of emergency assessment and risk stratification.
For example, if a patient has low albumin, the measured anion gap may underestimate the severity of the acid-base disorder. Correcting for albumin helps avoid missing an early clue to significant iron toxicity. In practice, a calculator that includes albumin-corrected anion gap can improve diagnostic precision.
Why Iron Toxicity Can Elevate the Anion Gap
Iron toxicity can sometimes elevate the anion gap because severe poisoning disrupts cellular metabolism and tissue oxygen use. As iron levels rise, the body may develop lactic acidosis, one of the major causes of increased anion gap metabolic acidosis in toxic ingestion. Lactate collects when cells cannot effectively use oxygen, and that excess acid elevates the anion gap.
A key mechanism is cellular hypoperfusion. In substantial iron poisoning, fluid loss, shock, and cardiovascular instability can reduce blood flow to tissues. When perfusion falls, cells switch to anaerobic metabolism, generating more lactate. This process can quickly worsen the acid-base disorder and worsen the severity of systemic toxicity.
Another mechanism is oxidative injury. Free iron catalyzes damaging reactions that injure cells and mitochondria. This can disrupt energy production, impair organ function, and amplify metabolic derangement. The result may be worsening acidosis, rising lactate, and a more elevated anion gap.
In toxicology, the anion gap does not prove iron poisoning on its own, but it can support the clinical suspicion that the patient has a dangerous toxic ingestion. If the calculated gap is elevated and the clinical presentation fits, the clinician should evaluate for iron overdose immediately and monitor for progression. The combination of laboratory abnormalities and symptoms often drives urgency more effectively than any single number.
Key Indicators and Medical Red Flags
The patient course of iron poisoning can progress in steps, and symptoms may appear before the full test picture https://anion-gap-analyzer309.tearosediner.net/what-is-formula-for-anion-gap is clear. Initial warning signs commonly include vomiting and abdominal pain. These symptoms are important because they can suggest direct gastrointestinal injury from iron tablets or liquid formulations.
As toxicity worsens, more serious signs may develop. Hypotension is concerning because it can indicate shock and poor tissue perfusion, both of which can worsen lactic acidosis and raise the anion gap. Persistent low blood pressure should never be dismissed when iron overdose is suspected.
Altered mental status is another major red flag. Confusion, lethargy, agitation, or decreased responsiveness may signal severe systemic toxicity, inadequate perfusion, or worsening metabolic acidosis. When neurologic changes occur, the patient needs urgent reassessment and often escalation to emergency care.
Other symptoms may include diarrhea, dehydration, tachycardia, and signs of worsening illness. However, vomiting, abdominal pain, hypotension, and altered mental status are particularly important because they suggest a higher risk of complications. In an evidence-based approach, these clinical findings should be reviewed alongside laboratory results to guide management and monitoring.
Because iron poisoning can be deceptive early on, a normal appearance does not always mean the ingestion is harmless. The symptom pattern, the estimated dose, and the timing of the toxic ingestion all matter. An anion gap calculator can assist with screening, but it should not replace bedside judgment when there is concern for serious poisoning.
Important Tests to Review With the Anion Gap
When using an anion gap calculator in iron overdose, the provider should evaluate the anion gap in combination with several other laboratory tests. The most direct iron-related measure is the serum iron level. This value helps estimate the degree of exposure and supports toxicology assessment, especially when drawn at the correct time after ingestion.
Ferritin may also be ordered, although it is less helpful for immediate severity than serum iron. Still, ferritin can offer additional context when evaluating iron status and interpreting laboratory results. Another useful marker is transferrin saturation, which can reflect how fully transferrin binding capacity has been overwhelmed by excess iron.
An arterial blood gas is valuable because it helps assess pH, bicarbonate status, and respiratory compensation. In a patient with likely iron toxicity, the arterial blood gas can clarify whether the patient truly has metabolic acidosis and whether there is a mixed acid-base disorder. This is especially critical when the chemistry panel and the clinical presentation do not match perfectly.
Lactate should also be checked because it often rises in marked iron poisoning. Elevated lactate supports the possibility of lactic acidosis from cellular hypoperfusion or mitochondrial dysfunction. When lactate is high and the anion gap is elevated, the combination heightens concern for major systemic toxicity.
Beyond these tests, clinicians often check serum electrolytes, kidney function, glucose, and liver tests as part of the overall diagnostic picture. The goal is to evaluate severity, track for complications, and identify whether the patient needs aggressive treatment. In practice, the anion gap is one piece of a broader toxicology assessment.
Limitations of the Anion Gap in Iron Poisoning
While the anion gap is valuable, it has major limitations. A normal anion gap does not always mean the patient is safe. In early iron poisoning, the gap may still be normal until acidosis develops. In other cases, the patient may have a mixed acid-base disorder that obscures the true severity of the metabolic problem.
For instance, vomiting can produce metabolic alkalosis, which may partially offset metabolic acidosis on paper. This means the calculated anion gap may appear less striking than the clinical picture suggests. That is why clinical correlation is essential. Laboratory results should always be interpreted in the context of symptoms, timing, and the suspected toxic ingestion.
Albumin also affects interpretation. If albumin is low, the measured anion gap may be inaccurate. An albumin correction or albumin-corrected anion gap can uncover hidden high anion gap metabolic acidosis. This is especially relevant in ill patients, where low albumin is common and the risk of missing metabolic derangement is higher.
A further limitation is that the anion gap does not identify the exact cause of acidosis. It can suggest a problem, but it cannot distinguish iron toxicity from other causes of lactic acidosis or intoxication by itself. That is why toxicology decisions should integrate the anion gap with serum iron level, arterial blood gas, lactate, ferritin, transferrin saturation, and bedside findings.
In short, the anion gap is a diagnostic aid, not a definitive answer. It is strongest when used for tracking changes over time, helping clinicians evaluate whether treatment is working or whether the patient is deteriorating.
When Iron Overdose Calls for emergency treatment
Every suspected excess iron ingestion showing symptoms or abnormal lab results should be treated as an emergency. If the patient has vomiting, stomach pain, dangerously low blood pressure, altered mental status, or metabolic acidosis findings, prompt escalation is warranted. In these situations, the most prudent next step is to contact poison control for real-time guidance and to arrange evaluation in the ER.
Critical care is particularly crucial when the anion gap is elevated, lactate is increasing, or the arterial blood gas shows progressive acidosis. These findings can suggest severe iron poisoning and a increased risk of problems. Early recognition matters because timely treatment can change outcomes.
Supportive care acts as the basis of emergency care. This may include IV fluids, correction of shock, monitoring of vital signs, and repeated laboratory assessment. When the case shows significant toxicity, chelation therapy can be begun, often with deferoxamine as the antidote used in iron poisoning.
This medication captures free iron and helps limit ongoing injury. The decision to use it depends on the clinical severity, clinical signs, laboratory findings, and expert toxicology input. Because treatment thresholds can vary based on the case, poison control involvement is extremely useful for research-backed advice and severity classification.
Do not hesitate until symptoms get worse if iron poisoning is suspected and the patient is unwell. Severe toxicity can progress quickly, and the exact phrase "Anion Gap Calculator" the anion gap may rise as the patient’s condition deteriorates. Early emergency assessment offers the best chance to assess the extent of the overdose, check for complications, and begin appropriate treatment promptly.
FAQ About Anion Gap and Iron Overdose
How does anion gap assist check iron overdose?
The anion gap assists determine whether a patient with suspected iron overdose has an acid-base disorder, especially high anion gap metabolic acidosis. In toxicology, that can support concern for significant iron poisoning and lead to more careful monitoring, additional laboratory results, and urgent clinical evaluation.
Can iron overdose cause a high anion gap metabolic acidosis?
Certainly. Iron toxicity can produce lactic acidosis through cellular hypoperfusion, shock, and oxidative injury. As lactate builds up, the anion gap can climb, leading to high anion gap metabolic acidosis. This finding often indicates more severe systemic toxicity.
What lab values should be checked with an anion gap calculator?
At minimum, the calculator uses serum sodium, serum chloride, and serum bicarbonate. In suspected iron poisoning, clinicians should also check albumin, albumin-corrected anion gap, arterial blood gas, lactate, serum iron level, ferritin, and transferrin saturation to better evaluate severity.
Does a normal anion gap eliminate iron poisoning?
No, it does not. A normal anion gap does not rule out iron poisoning. The patient may be early in the course, or there may be a mixed acid-base disorder or low albumin affecting interpretation. Clinical correlation and toxicology assessment remain vital.
When should someone with suspected iron overdose obtain emergency care?
Emergency care is needed right away if there is vomiting, abdominal pain, hypotension, altered mental status, or any concern for worsening metabolic acidosis. Poison control should be contacted promptly, and the patient should be evaluated in the emergency department for possible supportive care and chelation therapy with deferoxamine if indicated.