What’s an Anion Gap?
The gap calculation is a calculated measurement from routine blood tests that assists clinicians understand electrolytes and analyze acid-base balance. It is especially useful when reviewing metabolic acidosis, because it can point toward hidden acids in the bloodstream that are not directly measured on a usual blood chemistry panel or serum chemistry panel.
In plain terms, the anion gap compares measured positive charges, mainly sodium, with measured negative charges, mainly chloride and bicarbonate. If the gap is increased, it usually means extra acid is present, or bicarbonate has been used up while buffering acids in the body. That makes the anion gap a valuable diagnostic clue when reviewing blood test results.
The anion gap is not a standalone diagnosis by itself. It is a tool for clinical interpretation. A normal result does not rule out illness, and a high result does not automatically mean one specific condition. Instead, it helps focus the search for an underlying cause such as lactic acidosis, ketoacidosis, kidney disease, or toxin exposure.
An Anion Gap Calculator is used to perform this calculation efficiently and reliably. It helps clinicians and readers understand whether a value is within range or whether there is an elevated anion gap that needs closer attention.
Can Convulsions Increase the Anion Gap?
Indeed. A seizure can briefly increase the anion gap, typically because of a burst in lactic acid formation during intense body-wide exertion. This can cause anion gap metabolic acidosis that shows up soon after the event, especially if blood is drawn during the postictal state.
The key point is that this rise is often short-lived. After a generalized seizure, muscles work intensely and oxygen demand rises rapidly. If the body cannot keep up, it shifts toward oxygen-poor energy production, which increases lactate. That lactate can produce a temporary high anion gap and a reduced bicarbonate level.
Every seizure does not necessarily cause the same lab pattern. The size of the change depends on seizure duration, severity, whether there was associated breathing distress, and how quickly the patient returns to baseline. A brief seizure may cause only a small shift, while prolonged seizure activity or status epilepticus can produce more significant abnormalities.
This is why the Anion Gap Calculator can be helpful after a seizure: it offers a structured way to assess whether the lab change fits a typical post-seizure pattern or whether it suggests a more concerning metabolic problem.
How
The primary reason a seizure can raise the anion gap is anaerobic metabolism. During seizure activity, the muscles and brain use a great deal of energy very quickly. If oxygen delivery cannot match demand, cells rely more heavily on pathways that generate lactate. That process is a form of lactate production associated with low tissue oxygen and an oxygen deficit.
As lactate builds up, it contributes to lactate-related acidosis, a common cause of a metabolic derangement with an elevated anion gap. The body’s buffering system tries to neutralize the acid, often using bicarbonate. As bicarbonate falls, the measured gap can rise.
Low oxygen is not always severe or prolonged, but even brief oxygen shortage during intense muscular exertion can be enough to alter lab values. The combination of increased energy demand, transient oxygen mismatch, and rapid lactate generation explains why seizure-related lab changes often look like a temporary metabolic acidosis.
Other factors can contribute as well. Rapid breathing after a seizure, catecholamine surge, and dehydration may worsen the picture. But lactate is usually the main driver of the post-seizure elevated gap.
A seizure can create a short-term metabolic picture that looks alarming on labs, but the time course often helps distinguish a transient change from a dangerous ongoing disorder.How exactly does an Anion Gap Calculator Function
An anion gap calculator uses the anion gap formula to estimate the difference between measured cations and anions. The standard version uses sodium, chloride, and bicarbonate from a chemistry panel.
The formula is simple:
Anion gap = sodium - (chloride + bicarbonate)
This is easy to use because sodium, chloride, and bicarbonate are standard components of many lab panels. When the result is elevated, it suggests there are unmeasured acids in the blood, which is why the result often gets discussed alongside metabolic acidosis.
For example, if sodium is high-normal and bicarbonate is low after a seizure, the calculated gap may rise even if chloride does not change much. That pattern can happen because bicarbonate is being consumed while buffering lactate and other acids.
The calculator is not designed to replace a clinician’s judgment. It is meant to support lab interpretation. The most useful approach is to look at the anion gap together with the full serum chemistry panel, blood gas data, symptoms, and the clinical story. That combination helps separate a typical post-seizure change from a different cause of high-gap acidosis.
Further Changes in Lab Values After a Seizure
Following a seizure, several lab values may fluctuate temporarily. The most notable is often the lactate level, which can climb quickly and then decrease as the body clears it. This is one reason post-seizure blood testing can show a picture of transient acid buildup rather than a chronic disorder.
A venous blood gas may show decreased bicarbonate or an low pH shortly after seizure activity. An arterial blood gas can also reveal acid-base abnormalities, especially if there was breathing impairment, prolonged convulsions, or poor oxygenation. Both tests help determine the degree of metabolic acidosis and whether there is a respiratory component.
Serum bicarbonate often drops because it is used to buffer acid. That decrease can be a strong clue that the body recently experienced significant acid load. In some cases, the bicarbonate normalizes quickly as the postictal state resolves and lactate is metabolized.
These changes can be part of expected recovery after seizure activity, but they should always be interpreted in context. A mild abnormality that resolves with time is different from persistent acidosis or worsening symptoms.
When a High Anion Gap Is Concerning
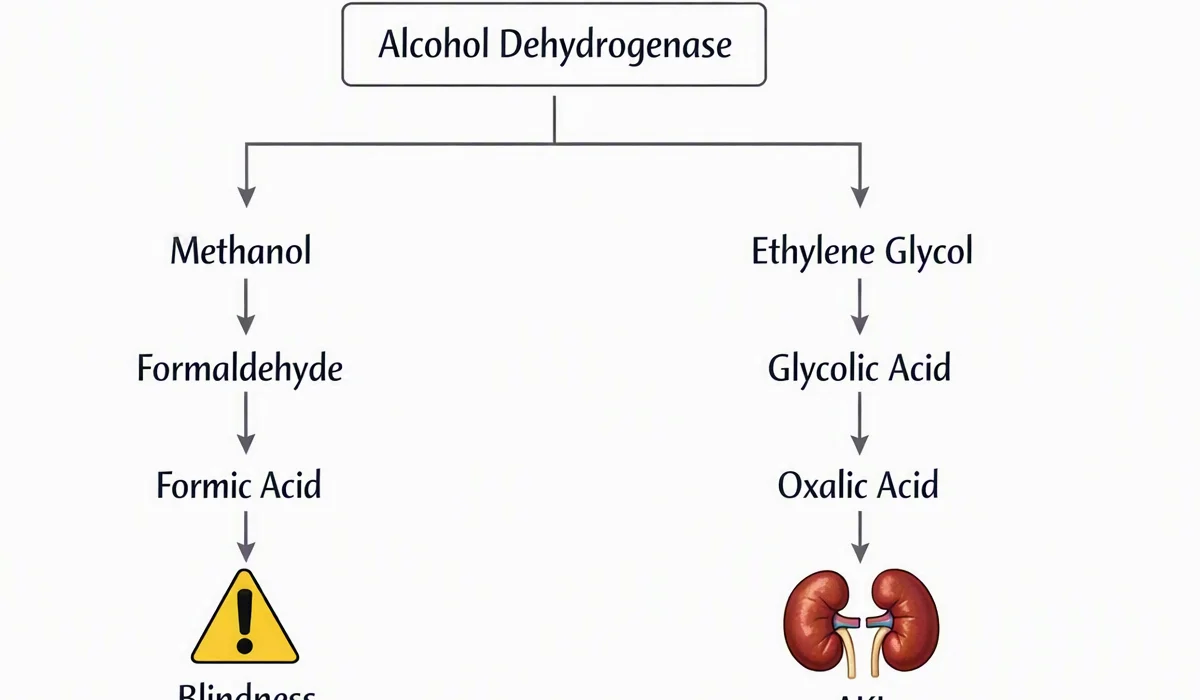
Even though a seizure can cause a short-lived rise, a persistently high anion gap should not be assumed to be benign. The list of causes includes significant sources of metabolic acidosis such as diabetic ketoacidosis, renal failure, and toxic alcohol ingestion.
They are significant because they can cause continued acid retention rather than a brief post-seizure change. For example, diabetic ketoacidosis often comes with hyperglycemia, dehydration, and ketosis. Renal failure can impair acid clearance. Toxic alcohol ingestion can create a hazardous metabolic profile that requires urgent treatment.
For this reason clinicians do not rely on the anion gap alone. They also review glucose, kidney function, ketones, osmolar gap when relevant, and the overall pattern of electrolyte imbalance. https://anion-gap-lookup590.wordcanopy.com/posts/can-the-anion-gap-be-normal-in-profound-acidosis If the blood gas shows ongoing acidosis or the patient remains ill, the cause may be a more serious issue than seizure recovery.
To put it another way, the elevated gap may be a post-seizure effect, but it can also be a diagnostic clue pointing to a different underlying problem. The distinction depends on the clinical picture and the course over time.
How Long the Anion Gap Stays Elevated After a Seizure
The length of time depends on postictal lactate clearance, the severity of the seizure, and the patient’s overall condition. In many cases, the time course is limited, and the gap starts improving as the patient enters clinical recovery. Lactate is often cleared relatively quickly once oxygen delivery and circulation normalize.
Since the increase is typically short-lived, repeat labs are often important. If the anion gap decreases and bicarbonate improves over a short interval, that favors a post-seizure explanation. If the gap does not normalize, keeps rising, or is accompanied by ongoing symptoms, another cause should be evaluated.
One of the most useful purposes of the Anion Gap Calculator is that it helps track whether the numbers fit the expected post-seizure pattern. A single elevated result matters less than the pattern. When the patient is awake, improving, and the labs are normalizing, the temporary increase is more likely to be part of the post-seizure process.
If the patient remains confused, short of breath, or unstable, the story changes. Persistent abnormalities suggest a larger metabolic issue that needs further workup.
When to Seek Medical Care
Medical care is urgent when seizure activity is lasting too long or when the patient does not return to baseline. Status epilepticus is a medical emergency because continuous or repeated seizure activity can worsen hypoxia, acidosis, and systemic stress.
Seek emergency evaluation if there is ongoing confusion, trouble breathing, cyanosis, repeated seizures, or failure to recover as expected. Shortness of breath after a seizure can signal respiratory compromise, aspiration, or another serious problem rather than a simple postictal state.
A high anion gap should also prompt urgent care if there are signs of diabetic ketoacidosis, toxic exposure, kidney failure, or severe dehydration. The concern is not just the number itself, but what it may mean. The lab value is a signal that should be interpreted with the symptoms, the blood gas, and the overall state.
When in doubt test again and quick clinical review are the best next actions. The combination of seizure recovery, lab trends, and symptom improvement usually clarifies whether the result was brief or concerning.
FAQ: Seizures and the Anion Gap
Can a seizure cause a high anion gap?
Indeed. Seizures can cause a temporary increase in the anion gap, usually from lactate buildup during severe seizure activity and the postictal state. This is a form of lactic acidosis and may appear as an elevated anion gap on a serum chemistry panel.
How high can the anion gap get after a seizure?
It can rise enough to look clearly abnormal, but the exact value depends on seizure duration, muscle activity, oxygen delivery, and how soon the blood was drawn. The Anion Gap Calculator helps with lab interpretation, but the trend over time and the clinical picture are more relevant than one isolated number.
How long does a seizure-related anion gap stay elevated?
Typically it is short-lived and improves as postictal lactate clearance occurs and clinical recovery begins. Repeat testing often shows improvement over a short time course. If the elevated anion gap persists, another underlying cause should be considered.
What labs usually change after a seizure?
The most common changes include a higher lactate level, lower serum bicarbonate, and abnormalities on venous blood gas or arterial blood gas testing. Sodium and chloride may be reviewed as part of the serum chemistry panel, because they are used in the anion gap formula.
When should a high anion gap after a seizure be evaluated urgently?
Urgent evaluation is needed if there is status epilepticus, confusion that does not improve, shortness of breath, persistent acidosis, or concern for diabetic ketoacidosis, renal failure, or toxic alcohol ingestion. Repeat labs and clinical assessment help determine whether the elevated anion gap is just post-seizure or something more serious.