
What the Anion Gap Assesses
The anion gap is a useful way to assess the balance of ions in the blood, especially when evaluating acid-base balance. It is calculated from routine serum electrolytes and helps clinicians calculate anion gap values as part of a more complete metabolic acidosis evaluation. In many cases, the calculation uses sodium, chloride, and bicarbonate from an electrolyte panel.
This number is not a literal measurement of acids. Instead of that, it reflects the amount of unmeasured anions in the blood. Those unmeasured substances can rise in metabolic acidosis, making the anion gap a useful diagnostic tool for detecting unexpected acidosis. It is especially useful when monitoring serum bicarbonate level changes that may indicate an acid-base https://anion-gap-tracker244.cavandoragh.org/what-does-anion-gap-mean-in-chemistry problem even before the full picture is obvious.
The anion gap is often used to help interpret lab results when the cause of acidosis is not clear right away. A high value can indicate extra acids in the blood, while a normal value can suggest other forms of acid loss or replacement. Because the calculation is based on everyday serum electrolytes, it is widely available and easy to follow over time.
How Albumin Affects the Anion Gap
Albumin is one of the primary protein bound anions in plasma, so it has a meaningful effect on the measured anion gap. When albumin is low, the gap may seem smaller than it really is because fewer negatively charged proteins are present to contribute to the total. This is why hypoalbuminemia can mask a true acid-base problem.
To account for this, clinicians use albumin correction to work out a corrected anion gap. This adjusted value is often called the albumin adjusted anion gap. It helps correct for albumin so that the result better represents the actual presence of unmeasured anions.
This correction matters because a normal-looking anion gap may not be truly normal when albumin is reduced. In patients with low serum albumin level, the uncorrected number can downplay the severity of metabolic acidosis. That means albumin adjustment improves the value of the result for clinical interpretation and may improve diagnostic accuracy.
In short, albumin changes the anion gap because it is a major contributor to the negative charge in plasma. If albumin falls, the measured gap often falls too, even when the underlying acid-base disorder has not improved.
How to Operate an Anion Gap Calculator
An Anion Gap Calculator makes easier the task of finding and refining the gap. To operate it, you generally enter the values for sodium, chloride, bicarbonate, and albumin. The calculator then uses the anion gap formula and, when needed, the albumin adjustment automatically.
The basic workflow is straightforward:
- Enter the sodium value from the lab report. Input chloride and bicarbonate values. Enter the albumin value if albumin correction is needed. Review the calculated anion gap and the corrected anion gap. Match the result with the reference range used by the lab.
This process allows clinicians and learners interpret lab results quickly, especially when evaluating acid base status. It also reduces arithmetic mistakes and promotes faster recognition of electrolyte imbalance patterns. For practical use, the calculator serves as a fast diagnostic tool that can help screen for hidden acidosis.
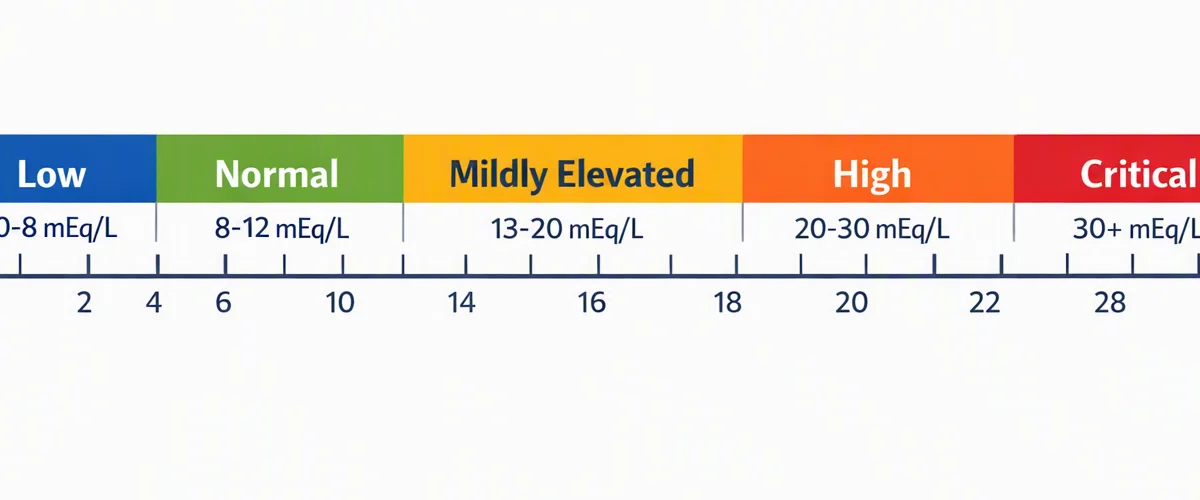
When reviewing the result, remember that the calculator is only one part of the overall picture. The numbers must still be interpreted in context with the patient’s symptoms, history, and other laboratory findings.
Anion Gap Assessment with Albumin Correction Formula and Step-by-Step Calculation
The usual anion gap formula is:
Anion gap = sodium − (chloride + bicarbonate)
The result is typically reported in mmol/L. The exact reference range can differ by laboratory method, but the calculation itself is simple and commonly used.
To apply albumin correction formula, a standard approach is to add a correction factor based on the patient’s albumin level. A common method adds approximately 2.5 mmol/L to the anion gap for every 1 g/dL decrease in albumin below normal. The specific method may vary by institution, so the laboratory reference range and local practice should always be checked.
A simple stepwise approach is as follows:
- Compute the initial anion gap using sodium, chloride, and bicarbonate. Assess the serum albumin level. If albumin is low, apply the albumin correction. Evaluate the albumin adjusted anion gap in mmol/L. Contrast both the raw and corrected values with the expected reference range.
Calculation example: If sodium is 140 mmol/L, chloride is 104 mmol/L, and bicarbonate is 20 mmol/L, the uncorrected anion gap is 16 mmol/L. If albumin is low, the corrected anion gap may be higher after adjustment, which could change the interpretation from borderline to clearly abnormal. That is why the calculator is helpful for both teaching and bedside clinical interpretation.
The purpose is not only to produce a number. It is to make the acid-base analysis more accurate by accounting for changes in protein bound anions that alter the baseline.
Interpreting High, Normal, and Low Anion Gap Findings
A elevated result often indicates high anion gap metabolic acidosis, which means extra acids or unmeasured anions are accumulating. This pattern usually calls for a targeted search for the cause, especially if the bicarbonate is low and symptoms match the pattern.
A normal result does not always exclude a problem. Normal anion gap metabolic acidosis can occur when bicarbonate is removed and replaced by chloride, leaving the calculated gap unchanged. In these cases, the acid-base disturbance is present, but the gap is not elevated. That is why the full lab pattern matters so much in clinical interpretation.
A low anion gap is less common but still worth noting. It can occur with low albumin, lab variation, or unusual positively charged substances. A low value should not be ignored, especially if the patient has other signs of electrolyte imbalance or a broader acid-base problem.
In practice, the interpretation depends on the relationship between the gap, bicarbonate, chloride, and albumin. This is where the Anion Gap Calculator becomes especially useful because it helps distinguish a truly normal value from one that only appears normal because of hypoalbuminemia.
Main interpretation points include:
- Elevated gap: think about extra acids and metabolic acidosis. Unchanged gap: look into bicarbonate loss or chloride replacement. Reduced gap: check albumin, method issues, and unusual lab patterns.
Common Causes of Unusual Anion Gap
Several conditions are closely linked to abnormal anion gap values. Certain conditions raise the gap because they increase acidity in the blood, while others decrease it indirectly by changing the protein or electrolyte balance.
Lactic acidosis is a well-known cause of high anion gap metabolic acidosis. When tissues are underperfused or oxygen delivery is limited, lactate accumulates and the gap rises. This is often seen in severe illness and is a major reason clinicians use the anion gap as part of metabolic acidosis evaluation.
Ketoacidosis is a further common cause. In diabetic, alcoholic, or starvation states, ketone bodies add to the pool of unmeasured anions, raising the gap. A high value in this setting often supports the diagnosis when the rest of the data fit.
Renal failure can also increase the gap because the kidneys do not eliminate acid efficiently. As acids accumulate, the bicarbonate falls and the gap may rise. This makes the anion gap a useful clue in chronic or acute kidney dysfunction.
Toxic alcohols are a key cause to consider. Certain ingestions produce organic acids that elevate the gap and can cause dangerous acid-base imbalances. In such cases, the anion gap may provide an early warning signal that requires urgent attention.
Further causes can include severe tissue hypoperfusion, sepsis, or mixed toxic exposures. Because multiple processes can overlap, the calculator should be used as part of a broader clinical interpretation rather than as a standalone answer.
When to Correct the Anion Gap for Albumin
Adjusting for albumin is especially important when hypoalbuminemia is detected. In patients with decreased albumin, the uncorrected anion gap may downplay the degree of acid accumulation, which can cause missed or delayed recognition of metabolic acidosis.
Correction is especially valuable in critical illness, where albumin often decreases and acid-base disorders are frequent. In this setting, relying on the raw number alone can weaken diagnostic accuracy. The adjusted value gives a clearer view of the true acid-base status and can help identify a hidden gap that would otherwise be overlooked.
It is also helpful when the clinical picture suggests acidosis but the measured gap looks normal. In such cases, albumin adjustment can help clarify the discrepancy and improve acid-base disorders assessment. This is one reason the calculator is often used to screen for hidden acidosis.
Situations where albumin correction is often helpful include:
- Decreased serum albumin level Critical illness Unclear acid-base balance abnormalities Likely unexpected acidosis with a borderline gap
In short, if albumin is low, the corrected value is usually the more meaningful clinical measure than the uncorrected one.
Limitations and Clinical Caveats
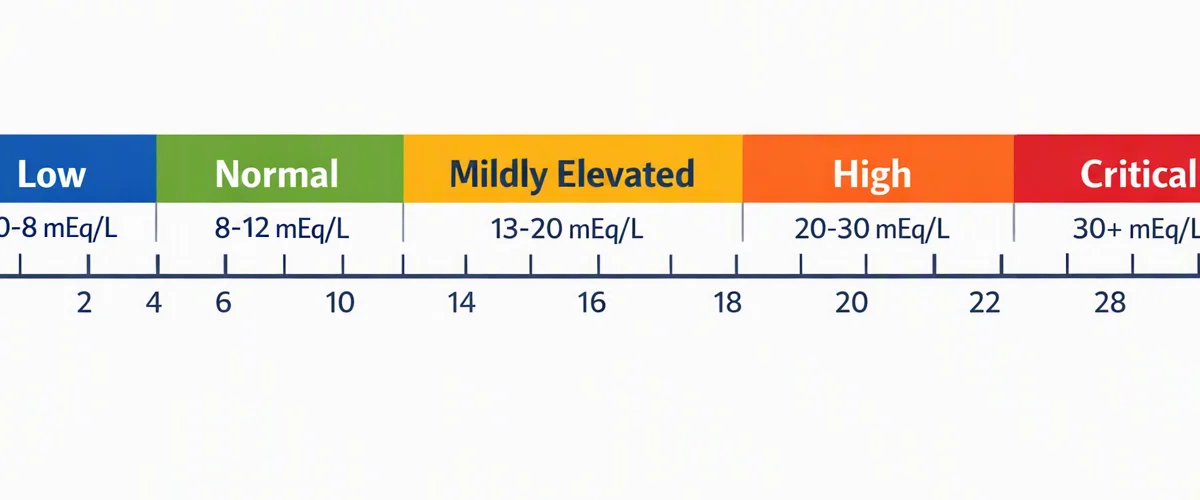
Although the anion gap is helpful, it has significant limitations. Various labs may use distinct measurement methods, which means lab variability can alter the result. A value that is acceptable in one setting may not be normal in another, so the local reference interval matters.
Another major caveat is the potential of a mixed acid-base disorder. A patient may have more than one process at the same time, such as a high-gap acidosis plus a metabolic alkalosis. In that situation, the bicarbonate and anion gap may not behave in a simple way, and careful analysis is essential.
Likewise, a broader electrolyte imbalance can skew the interpretation. Changes in sodium, chloride, or bicarbonate can shift the number even when the underlying clinical condition is complex. That is why the gap should always be interpreted alongside the full chemistry panel and clinical scenario.
Other caveats include unusual proteins, analytical differences, and the fact that albumin correction is an estimate rather than a perfect measurement. The adjusted result is helpful, but it is still only one part of a full acid-base evaluation.
Best practice is to use the calculator as a guide, then confirm the pattern against symptoms, history, and related laboratory findings. That approach improves confidence in the final clinical interpretation.
Frequently Asked Questions
What is an anion gap calculator used for?
An Anion Gap Calculator is used to determine and interpret the anion gap from common serum electrolytes. It helps clinicians evaluate acid-base balance, identify metabolic acidosis, and detect a possible hidden acid load when the routine lab pattern is not obvious.
How do you correct the anion gap for albumin?
To correct for albumin, first calculate the raw gap using sodium, chloride, and bicarbonate. Then apply an albumin correction factor based on the patient’s serum albumin level. Because low albumin lowers the measured gap, the adjustment produces a more precise corrected anion gap.
What’s a typical anion gap value range?
The anion gap reference range varies by the laboratory’s method and normal range. This is why it is necessary to interpret the result using the local laboratory reference range rather than relying on one universal number. The calculator lets you compare the result with the correct interval.
Why does low albumin lower the anion gap?
Albumin is a key source of negative charge in the blood because it contains protein bound anions. When albumin is low, there are less negative charges contributing to the gap, so the measured value decreases. This is why hypoalbuminemia can make the gap seem falsely low or low.
What disorders cause a high anion gap?
Frequent causes of a high gap include lactic acidosis, ketoacidosis, kidney failure, and toxic alcohols. These conditions add to unmeasured negative ions and often produce anion gap metabolic acidosis. The exact cause should be identified by the full clinical picture and supporting labs.